

You may have been told your child has a tongue tie, or maybe you have been piecing it together on your own after feeding trouble, clicking sounds during nursing, slow weight gain, messy eating, speech concerns, or a child who cannot seem to move their tongue the way other kids can. That kind of uncertainty sits with you, and even finding a pediatric dentist in Chandler can become part of the search for answers. It turns ordinary moments like feeding, brushing teeth, and mealtime into something tense.
A tongue tie assessment in pediatric dentistry is often one part of a bigger picture, not the whole picture by itself. A pediatric dentist can examine the frenum, tongue movement, oral development, and how those findings connect to daily function. Some children only need monitoring. Some benefit from treatment. Some need other specialists involved because feeding, speech, airway, and growth do not belong to one profession alone.
Pediatric tongue tie evaluations focus on function, not just appearance
A tongue tie, also called ankyloglossia, happens when the tissue connecting the tongue to the floor of the mouth limits movement. The key issue is not whether the frenum looks short or thick. The key issue is whether your child can use their tongue well enough for feeding, swallowing, cleaning food from the teeth, speech development, and normal oral function. MedlinePlus explains ankyloglossia in simple terms, and that basic definition helps, but a real assessment goes further.
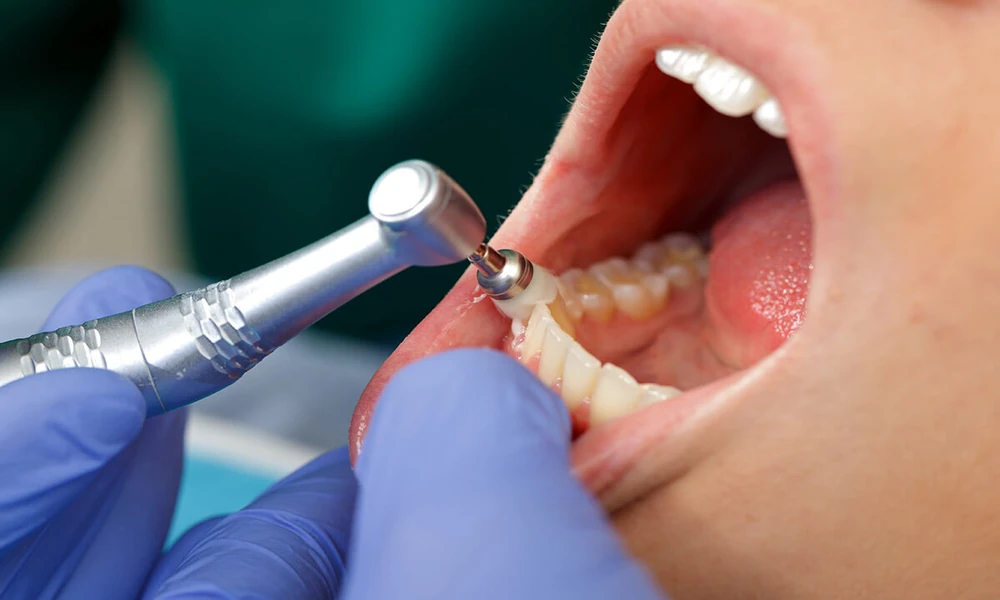
In pediatric dental care, the exam usually includes tongue lift, extension, side to side movement, latch history, oral habits, palate shape, gum health, and signs of strain in the lips, jaw, or cheeks. A child can have a visible tongue tie and function well. Another child can have a less obvious restriction and still struggle every day. That mismatch is where many families get frustrated. You may hear one person say it is nothing, then another says it explains everything. The truth is often in the middle.
Pediatric dental tongue tie assessments matter because they look at what your child is actually doing with their mouth, not just what a quick glance shows. That can prevent overtreatment, but it can also prevent months of waiting when a child clearly needs help.
Other specialists may be involved when symptoms reach beyond the mouth
Many families expect one appointment to settle the issue. Sometimes it does. Sometimes it opens the door to a team approach because the symptoms cross into feeding, speech, airway, or medical care.
A lactation consultant may be involved for an infant who cannot maintain a latch, tires during feeds, or causes ongoing pain with nursing. A speech language pathologist may assess oral motor patterns, swallowing, and speech sound production in an older child. An ear, nose, and throat physician or oral surgeon may be part of care when anatomy is more complex, when surgery needs to be considered, or when there are airway concerns. A pediatrician may help rule out other causes of poor feeding, reflux, weight issues, or delayed growth.
This matters because tongue tie symptoms can overlap with many other problems. A baby who feeds poorly may also have reflux, muscle tension, prematurity related challenges, or a high palate. A child with unclear speech may have age typical sound errors, hearing issues, or a motor planning disorder. If treatment is done without sorting through those factors, parents can end up disappointed, confused, and paying for care that does not solve the real problem.
The American Academy of Pediatric Dentistry policy on frenulum management supports careful diagnosis and coordinated care. That means treatment decisions should be based on symptoms and function, with input from other professionals when needed.
Signs that a pediatric dentist may refer to another specialist
Referral is not a bad sign. It usually means the exam is being taken seriously. A pediatric dentist may bring in another specialist when feeding problems are significant, weight gain is a concern, speech issues are not straightforward, oral anatomy is unusual, or there are signs of sleep disordered breathing. A child who gags often, mouth breathes, snores, or struggles with textured foods may need a wider evaluation.
Some children also need support before and after any procedure. If the tongue has been restricted for a long time, movement patterns may not improve overnight. Oral exercises, feeding therapy, or speech therapy may help the child learn to use that new range of motion. Parents are often surprised by that. They expect the release, if one is recommended, to be the finish line. It is often one step in a process.
Comparison points that help families decide what comes next
| Situation | Pediatric Dentist Role | Other Specialist Who May Help | Why Team Care Matters |
|---|---|---|---|
| Infant has painful latch and poor milk transfer | Examines oral restriction and tongue function | Lactation consultant, pediatrician | Feeding issues may involve latch mechanics, supply, weight gain, and oral restriction together |
| Toddler has trouble chewing and managing textured foods | Checks mobility, bite, palate shape, and oral habits | Feeding therapist, speech language pathologist | Function may need therapy, not just a procedure |
| Child has speech concerns | Assesses whether restriction may affect oral movement | Speech language pathologist, pediatrician | Not all speech errors come from tongue tie |
| Snoring, mouth breathing, restless sleep | Looks for oral signs linked to airway development | ENT, pediatrician, sleep specialist | Airway concerns should not be reduced to one oral finding |
| Family is unsure whether treatment is needed | Provides a structured tongue tie evaluation | Varies by symptoms | A clear diagnosis can prevent unnecessary treatment or delay |
Clear steps you can take right now
Track function, not just appearance. Write down what is happening day to day. Note feeding time, pain with nursing, clicking, leaking milk, gagging, food refusal, speech concerns, snoring, or frustration during brushing. Those details help a pediatric dentist see patterns that a quick office snapshot can miss.
Ask for a full pediatric dentist exam. A good visit should cover tongue mobility, oral development, symptoms, and whether a referral makes sense. If you leave with only a label and no explanation of function, you still do not have the answer you need.
Build the right team early. If your child has feeding, speech, or airway symptoms, ask whether a lactation consultant, speech language pathologist, ENT, or pediatrician should be involved. Early team care often shortens the path to real improvement.
The right assessment can bring clarity and relief
You do not need to guess your way through this. If something has felt off with feeding, speech, or oral function, there is a reason to have it checked. A thoughtful pediatric dentist can help sort out whether tongue tie is the main issue, a contributing issue, or not the issue at all, and whether another specialist should step in. That kind of clarity can ease a lot of stress and help you make the next decision with confidence.
